OVERLAY AND PHR
Add capability. Replace nothing.
- EHR stays the record
- PHR for the patient
- One FHIR contract
Your record stays in the system your team knows. Hilbi reads through FHIR, adds the pathway on top, and writes results back. No migration. No parallel record.
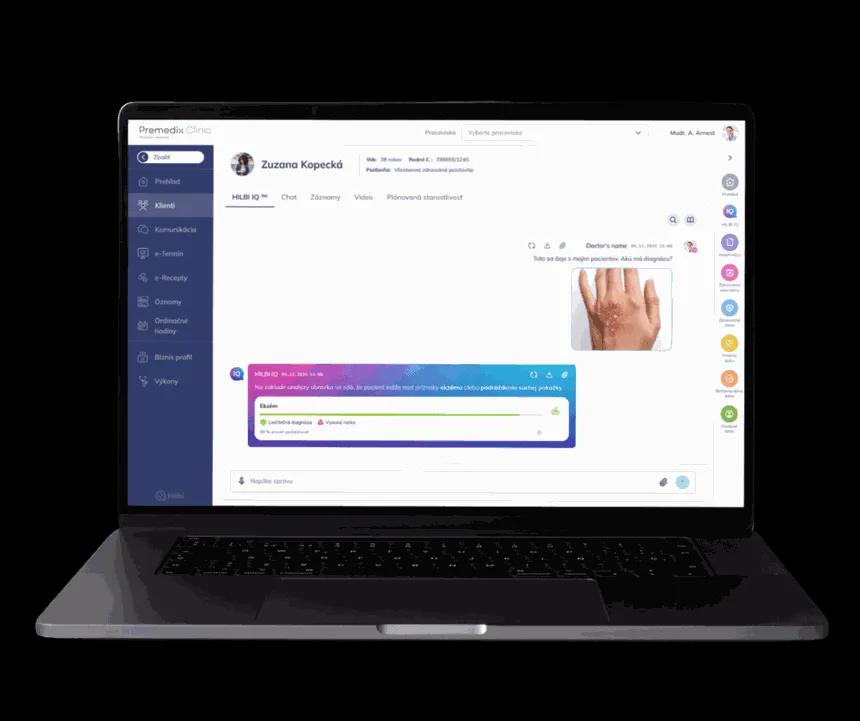
Above your system
nothing is migrated
Your record stays yours
we never become the system of record
This is the question that ends most evaluations
Replacing a system of record is a migration project with a clinical risk profile, a procurement cycle and a training bill. It is why most digital-health evaluations end before they begin. Hilbi does not ask for it. The record stays where it is today, under the law that governs it today, and the capability is added above it.
Two records, two roles
The distinction is legal as much as technical, and it is what makes the model work across providers.
Your EHR stays the record
The health record is the provider's, under Act 576/2004 Coll. and Act 372/2011 Coll. Hilbi reads and writes through FHIR R4 and never becomes it.
Hilbi holds the patient's record
A personal health record is a different legal object. It is the patient's, and it is how they exercise access and portability.
The patient is the only constant
A record anchored to the patient stays whole where an institutional record stops at the institution's edge. Consent travels with it.
One contract, any system
One FHIR R4 resource contract whatever sits behind it, so a new market is a connector and a configuration, not a rebuild.
The overlay, stated as facts
What Hilbi masters, what your record system masters, and what never moves.
- PositionIn force
- An orchestration layer above the existing record system. Never the system of record.
- What Hilbi mastersIn force
- Plan definitions, patient-reported data, and the patient's own personal health record.
- What the record system mastersIn force
- The clinical record, under Act 576/2004 Coll. in Slovakia and Act 372/2011 Coll. in Czechia.
- InterfaceIn force
- HL7 FHIR R4; ISO 13606 semantics for synchronisation with local systems.
- Basis of the patient's recordIn force
- The patient's own; consent travels with it between providers and borders.
- Synchronisation readinessReadiness
- Stapro, CGM, Epic: readiness declared; live status per system.
- Backbone modeIn force
- Where standardisation is required, Hilbi can operate as the core patient platform.
- Data residencyIn force
- Stated per market; never one global claim.
- What it does not doIn force
- No migration, no parallel record, no moment where clinical data is in two places at once.
- ExitIn force
- Your record never left your system. Audit log exportable; patient-held data exports as a FHIR R4 bundle.
What the connection model is ready for
Readiness is declared here. Whether a connection is live is a separate statement, made per system.
- Stapro and CGM are live at named sites in Slovakia and Czechia.
- Epic is live at one international site and readiness is declared for the rest.
- Every live connection is listed with its agreed scope on the integrations page.
- StaproCzechia, Slovakia · HL7 FHIR R4, mapped from the local recordReadiness declared
- CGMCzechia, Slovakia, DACH · HL7 FHIR R4, mapped from the local recordReadiness declared
- EpicUnited States, international · HL7 FHIR R4Readiness declared
- Live connection status per systemAll markets · Published on each system's integration pagePublished
Questions about the overlay model
No. The clinical record stays in the system that holds it. Hilbi reads through HL7 FHIR R4, adds the coordination and patient-facing layer, and writes structured results back.
No, and it is designed so it cannot become one. The provider's record stays the provider's; what Hilbi holds is the patient's personal health record and the plan definitions above it.
The EHR record is the provider's, created under national health-record law and kept by the provider. The personal health record is the patient's: the patient decides who sees it, it follows them between providers, and it is the surface through which access and portability are exercised.
Regulation (EU) 2025/327 gives patients access to and portability of their electronic health data for primary use, and routes secondary use through Health Data Access Bodies with a permit. A patient-held record is the natural surface for the first and keeps the second consent-based and auditable.
Yes. The claimed listing, booking and patient-facing steps run before any connection exists; the connection adds write-back into the record you already keep.